
Medically reviewed by: Health is Heaven Medical Review Board | Published by Ganesh G Kamble, Health is Heaven | Published: April 19, 2026 · Last updated: August 21, 2026
A normal blood pressure reading for most healthy adults is below 120/80 mmHg. Readings of 120–129 systolic with diastolic under 80 are classified as "elevated," 130/80 mmHg or higher is high blood pressure (hypertension), and 180/120 mmHg or higher is a hypertensive crisis requiring immediate medical attention.
Blood pressure is a fundamental marker of cardiovascular function, representing the lateral force exerted by circulating blood against the vascular walls. Referencing a blood pressure chart by age is critical for identifying potential hypertensive trends and preventing cumulative shear stress on the endothelial lining of the arterial system. For individuals looking to stabilize their numbers, structured strategies for managing high blood pressure naturally or preparing meals from our list of low sodium recipes for heart health are highly effective. The landmark Systolic Blood Pressure Intervention Trial demonstrated that targeting a systolic pressure below 120 mmHg reduced the rates of cardiovascular events by 25 percent and the risk of death by 27 percent compared to a target of 140 mmHg. This clinical guide details the biophysical regulation of blood pressure, outlines age-stratified reference thresholds, and provides evidence-based home tracking protocols.
To accurately interpret your individual blood pressure measurements and determine their corresponding clinical categories immediately, you can utilize our blood pressure calculator. This tool is designed to cross-reference your numbers with the latest diagnostic criteria to help you track your cardiovascular trends over time.
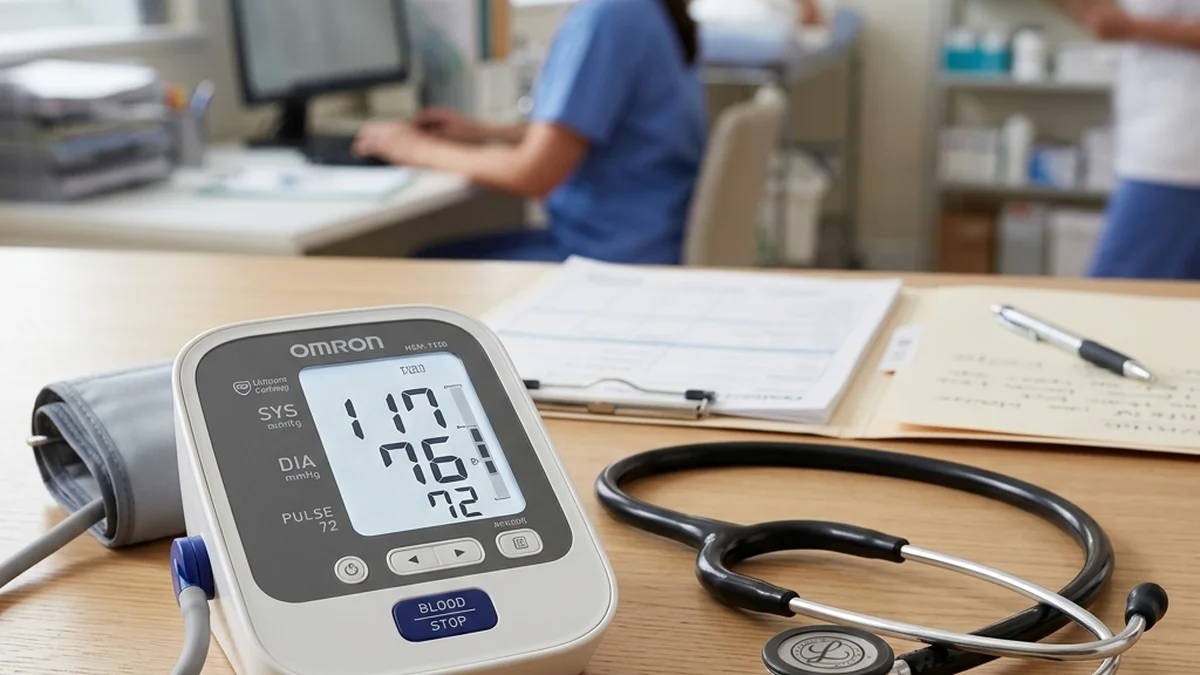
What Is Blood Pressure? (How It Is Measured)
The physics of blood flow is governed by fluid dynamics, primarily described by the equation where blood pressure is the product of cardiac output and total peripheral resistance. Cardiac output represents the volume of blood pumped by the left ventricle per minute, calculated as stroke volume multiplied by heart rate. Total peripheral resistance is the cumulative resistance offered by the systemic vasculature, primarily determined by the diameter of small arteries and arterioles. According to Poiseuille's Law, vascular resistance is inversely proportional to the fourth power of the vessel radius. Consequently, even minor reductions in arterial lumen diameter caused by vasoconstriction or plaque accumulation trigger substantial increases in systemic blood pressure.
Systolic blood pressure represents the peak force registered during ventricular contraction (systole), when the heart ejects a bolus of blood into the aorta. This number is heavily influenced by stroke volume, ejection velocity, and the compliance of the large elastic arteries. Diastolic blood pressure represents the minimum force registered during ventricular relaxation (diastole), reflecting the baseline vascular tension maintained by the recoil of elastic arteries and the resistance of peripheral arterioles. Together, these numbers dictate the mean arterial pressure, which is the average perfusion pressure driving blood into capillaries throughout the cardiac cycle. Mean arterial pressure is calculated as diastolic pressure plus one-third of the pulse pressure, which is the difference between systolic and diastolic numbers.
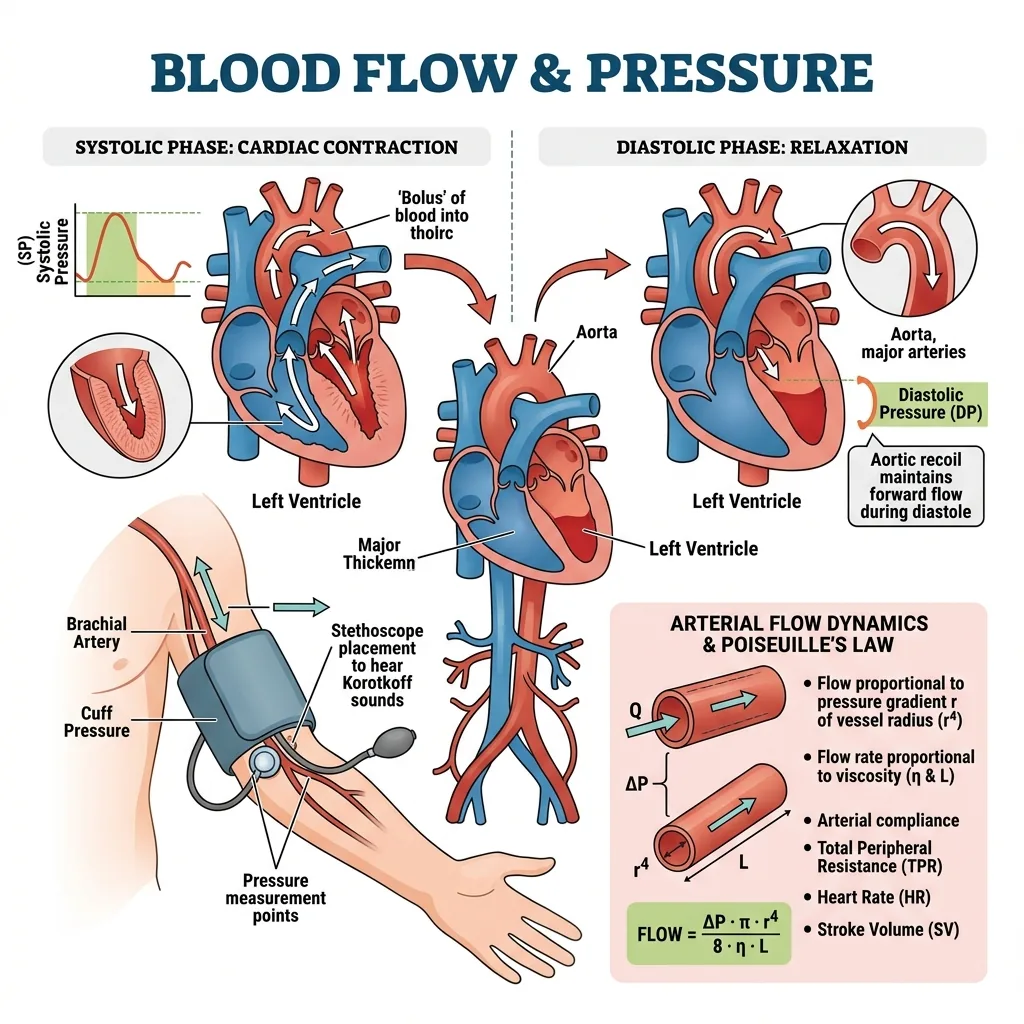
Vascular compliance is the ability of an artery to expand and contract in response to pressure changes. Under normal conditions, the aorta and large arteries act as an elastic reservoir, stretching during systole to absorb kinetic energy and recoiling during diastole to maintain continuous forward blood flow. As individuals age, or under the influence of chronic inflammation and oxidative stress, the elastic fibers within the arterial media layer degrade and are replaced by rigid collagen fibers. This process of arteriosclerosis reduces compliance, causing the systolic pressure to rise as the rigid walls can no longer expand, while the diastolic pressure falls because the lack of elastic recoil fails to sustain baseline tension. This combined shift results in an elevated pulse pressure, which is a major clinical marker for arterial aging (a process detailed in our overview where the science of biological aging explained clarifies structural media degradation) and stroke risk.
What Controls Your Blood Pressure?
The human body employs rapid neural pathways and long-term hormonal systems to calibrate systemic blood pressure, ensuring adequate perfusion to vital organs under varying postural and environmental conditions. The rapid neural response is managed by the autonomic nervous system through the baroreceptor reflex. Baroreceptors are specialized stretch-sensitive mechanoreceptors located in the carotid sinuses and the aortic arch. When blood pressure rises, these receptors stretch, increasing the frequency of action potentials sent via the glossopharyngeal and vagus nerves to the nucleus tractus solitarius in the brainstem medulla. The medulla responds by upregulating parasympathetic output via the vagus nerve to slow the heart rate, while simultaneously suppressing sympathetic output to the heart and systemic arterioles, causing vasodilation and bringing pressure back to baseline.
Conversely, when a person stands up rapidly, gravity causes blood to pool in the lower extremities, reducing venous return and cardiac output. This sudden drop in pressure decreases baroreceptor stretch, reducing their firing rate. The medulla responds by increasing sympathetic output, causing rapid vasoconstriction of arterioles, venoconstriction to increase venous return, and an increase in heart rate. This compensatory mechanism prevents orthostatic hypotension, which is a drop in blood pressure that can cause dizziness or fainting. In individuals with autonomic neuropathy, such as those with advanced diabetes, this reflex is impaired, leading to severe orthostatic instability.
Long-term blood pressure calibration is primarily regulated by the endocrine kidneys through the Renin-Angiotensin-Aldosterone System, abbreviated as the RAAS pathway. A fall in systemic blood pressure, a decrease in sodium delivery to the macula densa cells of the distal tubule, or direct sympathetic stimulation of renal nerves triggers the juxtaglomerular cells in the kidneys to secrete the enzyme renin into the bloodstream. Renin cleaves angiotensinogen, a glycoprotein synthesized by the liver, to produce the inactive decapeptide angiotensin I. As angiotensin I circulates through the pulmonary capillaries, it is cleaved by angiotensin-converting enzyme, which is primarily anchored to the vascular endothelium of the lungs, to form the active octapeptide angiotensin II.
Angiotensin II is a highly potent vasoconstrictor that binds to angiotensin II type 1 receptors on vascular smooth muscle cells, initiating an intracellular signaling cascade that leads to calcium influx and immediate arteriole constriction. Angiotensin II also acts directly on the adrenal cortex to stimulate the synthesis and release of aldosterone, a steroid hormone. Aldosterone travels to the kidneys, where it binds to mineralocorticoid receptors in the principal cells of the collecting ducts, upregulating the expression of epithelial sodium channels and sodium-potassium ATPase pumps. This genetic expression increases sodium reabsorption from the urine back into the blood, dragging water along osmotically. This process expands extracellular fluid volume, raises blood volume, and increases cardiac output, elevating systemic pressure. Additionally, angiotensin II stimulates the hypothalamus to release arginine vasopressin from the posterior pituitary, prompting the kidneys to reabsorb free water through aquaporin-2 channels and further expanding blood volume.
What Are the Normal Blood Pressure Ranges?
The standard reference framework for diagnosing and managing cardiovascular risk is defined by the American Heart Association and the American College of Cardiology. Revised in 2017, these categories lowered the threshold for diagnosing hypertension to identify early-stage vascular damage and encourage early lifestyle intervention. Because of these tighter metrics, many individuals face a sudden high blood pressure life insurance decline during underwriting. If you have dependents, you should also learn how to choose health insurance plan for family coverage. The diagnostic categories are structured as follows:
| Diagnostic Category | Systolic Range (mmHg) | Diastolic Range (mmHg) | Clinical Action Guidelines |
|---|---|---|---|
| Normal | Less than 120 | and Less than 80 | Maintain healthy lifestyle habits; complete an annual clinical check. |
| Elevated | 120 to 129 | and Less than 80 | Implement non-pharmacological lifestyle modifications; re-evaluate in 3 to 6 months. |
| Stage 1 Hypertension | 130 to 139 | or 80 to 89 | Assess cardiovascular risk; initiate lifestyle modifications; consider medication for high-risk patients. |
| Stage 2 Hypertension | 140 or Higher | or 90 or Higher | Initiate combination therapy (lifestyle + 1 or 2 medications); re-evaluate monthly. |
| Hypertensive Crisis | Higher than 180 | and/or Higher than 120 | Verify numbers immediately; if high, contact emergency services or seek urgent care. |
A hypertensive crisis requires immediate medical attention. When readings exceed 180 mmHg systolic or 120 mmHg diastolic, the patient is at acute risk for target organ damage, including intracranial hemorrhage, acute myocardial infarction, aortic dissection, or acute renal failure. If these numbers are accompanied by symptoms such as severe headache, chest pain, dyspnea, vision changes, or neurological deficits, emergency medical services must be contacted immediately. In the absence of symptoms, this is classified as hypertensive urgency, requiring prompt adjustment of medication under close medical supervision.
It is important to note that international diagnostic thresholds vary slightly. The European Society of Cardiology and the World Health Organization maintain a threshold of 140/90 mmHg for the formal diagnosis of hypertension. These agencies categorize readings between 130/85 and 139/89 mmHg as high normal blood pressure. Regardless of the regional nomenclature, clinical evidence consistently demonstrates that vascular risk begins to climb continuously once systolic pressures exceed 115 mmHg, making early cardiovascular tracking essential.
What Is Normal Blood Pressure by Age?
The clinical target for a healthy adult is the same at every age: under 120/80 mmHg, per the 2017 ACC/AHA guideline. What changes with age is the population average, since arteries naturally stiffen over time. The table below shows typical readings from birth through the senior years, sourced to CDC and American Academy of Pediatrics data. If you want to check where your own numbers land, run them through our free blood pressure checker.
| Life Stage | Typical Reading (Systolic/Diastolic, mmHg) | Clinical Target or Category |
|---|---|---|
| Newborn (0 to 1 month) | About 60 to 90 / 30 to 60 | Monitored by your baby's care team, not a home-cuff context |
| Infant (1 to 12 months) | About 75 to 105 / 35 to 70 | Same as above |
| Early childhood (1 to 5 years), 50th percentile | Boys: 86 to 94 / 41 to 53 Girls: 86 to 93 / 43 to 55 | Depends on age, sex, and height; a pediatrician plots the exact percentile |
| School age (6 to 12 years), 50th percentile | Boys: 95 to 104 / 56 to 62 Girls: 94 to 105 / 56 to 62 | Same as above |
| Teens (13 to 17 years) | Same categories used for adults apply from age 13 | Normal: under 120/80. Elevated: 120 to 129/under 80. Stage 1: 130 to 139/80 to 89. Stage 2: 140/90 or higher |
| Young adults (18 to 39) | Men: about 119/70 Women: about 110/68 | Under 120/80, same as every adult age |
| Midlife (40 to 59) | Men: about 124/77 Women: about 122/74 | Under 120/80 |
| 60 and older | Men: about 133/69 Women: about 139/68 | Often individualized; many clinicians target under 130/80 when safe to do so |
| 80 and older | No reliable population average is published at this age | Individualized target set with your own clinician, per 2017 ACC/AHA guidance |
Sources: CDC National Health Statistics Report No. 35 (adult NHANES data); 2017 American Academy of Pediatrics Clinical Practice Guideline (children and teens). Childhood figures are 50th-percentile ranges across the stated age span, not single-year values. Population averages, not personal targets.
As vascular structures transition through the aging process, the gradual increase in average systolic pressure is primarily driven by arterial stiffening. The continuous pulsatile flow generated by the heart over decades slowly breaks down the elastin fibers in the medial layer of the aorta, leading to a compensatory increase in collagen deposition. This structural remodeling increases pulse wave velocity, meaning the pressure wave generated by cardiac ejection travels faster through the arterial tree, reflecting back to the heart during systole rather than diastole. This amplification increases the workload on the left ventricle, causing left ventricular hypertrophy, while lowering diastolic pressure, which can compromise coronary artery perfusion since coronary arteries receive their blood flow during diastole.
For elderly patients, particularly those over the age of 70, clinical guidelines allow for a slightly higher systolic target (such as below 130 or 140 mmHg) to prevent the risk of cerebral hypoperfusion, orthostatic hypotension, and fall-related injuries. Tight control in frail older adults can lead to orthostatic intolerance, potentially causing syncope when standing. Clinicians carefully balance the prevention of long-term stroke risk with the immediate safety of the patient, frequently individualizing medication targets based on frailty, comorbidities, and overall functional status.
No major health survey publishes a distinct population-average reading for ages 80, 90, or 100. NHANES, the source behind most "average blood pressure by age" charts, tops out at a single "60 and older" bucket. Past that point, there simply isn't a large enough distinct sample to report a meaningful average, so clinicians work from individualized targets instead of a population number.
Is Blood Pressure Different for Men and Women?
Vascular dynamics differ significantly between sexes, shaped by distinct hormonal influences and physiological stages. Prior to menopause, women typically display lower systolic blood pressures than men of the same age. This difference is largely attributed to the vascular protective effects of estrogen. Estrogen stimulates endothelial nitric oxide synthase, which increases the production of nitric oxide, a potent local vasodilator. Nitric oxide diffuses into vascular smooth muscle cells, activating guanylyl cyclase to increase cyclic GMP, which promotes calcium extrusion and smooth muscle relaxation, lowering systemic resistance. Estrogen also dampens the activity of the sympathetic nervous system and suppresses the renin-angiotensin-aldosterone system, preventing excessive volume expansion.
Following menopause, the sharp decline in circulating estrogen levels removes these protective mechanisms, causing a rapid increase in systemic vascular resistance. As a result, post-menopausal women frequently experience a steep rise in blood pressure, often matching or exceeding the hypertension rates observed in men of the same age. Post-menopausal vascular changes are also marked by an increase in sympathetic tone, greater sensitivity to dietary sodium, and accelerated arterial stiffening, making routine cardiovascular screening vital during this life transition. Additionally, incorporating structured cardiovascular nutrition guidelines for lipid control can mitigate the risk of concurrent dyslipidemia and atherosclerosis in this population.
Pregnancy represents a unique vascular state characterized by a substantial expansion of blood volume and a compensatory drop in systemic vascular resistance. Progesterone and estrogen induce significant vasodilation, causing blood pressure to decline during the first and second trimesters, typically reaching a nadir at approximately 20 weeks of gestation before gradually returning to pre-pregnancy baselines in the third trimester. However, a failure of normal vascular adaptation can trigger gestational hypertension or preeclampsia, which is a multisystem disorder characterized by new-onset hypertension (above 140/90 mmHg) and proteinuria after 20 weeks of gestation. Preeclampsia is driven by abnormal placental vascular remodeling, leading to systemic endothelial dysfunction, microvascular damage, and organ perfusion failure, requiring immediate obstetric care.
What Causes High Blood Pressure?
Hypertension is categorized based on its underlying cause, with essential and secondary forms displaying different pathological mechanisms. Essential hypertension, also known as primary hypertension, accounts for approximately 90 to 95 percent of all clinical cases. It is a multifactorial condition that develops gradually over years, driven by a complex interaction of genetic predispositions and environmental factors. Key mechanisms of primary hypertension include:
- Visceral Adiposity: Excess visceral fat acts as an active endocrine organ, releasing pro-inflammatory cytokines like interleukin-6 and tumor necrosis factor-alpha. These markers trigger vascular inflammation, impair endothelial function, and stimulate the sympathetic nervous system, increasing cardiac output and arterial tension. You can calculate your weight parameters and calorie requirements using our calorie calculator for daily needs and check your baseline metrics with the bmi calculator for adults.
- Sodium-Potassium Imbalance: A high-sodium diet expands blood volume, while a low-potassium diet impairs the kidneys' ability to excrete sodium. Potassium also plays a direct vascular role by hyperpolarizing vascular smooth muscle cells, causing vasodilation. A lack of dietary potassium prevents this relaxation, increasing peripheral resistance.
- Sympathetic Overactivity: Chronic psychological stress, poor sleep, and sedentary habits lead to sustained sympathetic nervous system activation. This pathway increases heart rate and arteriole constriction through norepinephrine release, raising baseline pressure.
Secondary hypertension accounts for the remaining 5 to 10 percent of cases, characterized by a sudden, severe elevation in blood pressure caused by an identifiable underlying medical condition. Recognizing secondary hypertension is critical, as treating the primary condition can often cure or significantly improve the elevated pressure. Major causes of secondary hypertension include:
- Renal Artery Stenosis: Narrowing of one or both renal arteries, typically due to atherosclerosis or fibromuscular dysplasia, restricts blood flow to the kidneys. The affected kidney perceives this hypoperfusion as low systemic blood pressure, triggering an overproduction of renin. This excess renin drives systemic vasoconstriction and volume expansion, causing severe hypertension.
- Chronic Kidney Disease: Glomerular damage impairs the kidneys' ability to excrete sodium and water, leading to direct volume overload and elevated cardiac output.
- Primary Aldosteronism: An adrenal adenoma or bilateral adrenal hyperplasia causes autonomous, excessive secretion of aldosterone. This excess hormone drives continuous sodium and water retention in the renal collecting ducts, causing severe, treatment-resistant hypertension, often accompanied by low blood potassium levels (hypokalemia).
- Pheochromocytoma: A rare neuroendocrine tumor of the adrenal medulla that secretes large amounts of catecholamines (epinephrine and norepinephrine), causing paroxysmal surges in blood pressure, tachycardia, and headaches.
How Do You Take Blood Pressure at Home? (Step-by-Step)
Relying solely on office measurements can lead to diagnostic errors, as blood pressure fluctuates in response to acute stressors. Up to 30 percent of patients display white-coat hypertension, where readings are elevated in a medical setting but normal at home. Conversely, others experience masked hypertension, where office readings are normal but home or ambulatory readings are elevated, exposing them to hidden cardiovascular risk. Ambulatory and home tracking provide a more accurate representation of baseline vascular tension.

To ensure diagnostic accuracy when monitoring blood pressure at home, patients should adhere to the following clinical preparation protocol:
- Equipment Selection: Utilize an automatic, digital upper-arm cuff monitor that has been clinically validated. Avoid wrist monitors, as they are highly sensitive to arm positioning and frequently yield inaccurate readings. Ensure the cuff size matches your arm circumference; a cuff that is too small will artificially overestimate pressure, while one that is too large will underestimate it.
- Preparation Phase: Avoid consuming caffeine, smoking nicotine, or engaging in physical exercise for at least 30 minutes prior to taking a reading. Empty your bladder completely before measurement, as a full bladder can elevate systolic pressure by up to 10 to 15 mmHg through sympathetic reflex activation.
- Postural Alignment: Sit quietly in a supportive chair with your back resting against the backrest and both feet flat on the floor. Do not cross your legs, as crossing them at the knees can temporarily compress femoral veins, increasing venous return and elevating systolic readings by 2 to 8 mmHg. Rest your arm on a flat surface, such as a table, ensuring the midpoint of the cuff is positioned at heart level.
- Measurement Protocol: Remain completely still and do not speak during the test, as active conversation can raise readings by 10 mmHg. Take two measurements spaced one to two minutes apart, record the values, and calculate the average. Maintain this tracking routine twice daily, in the morning before medication and in the evening before dinner, keeping a log for seven consecutive days to establish a reliable baseline.
When Should You Call a Doctor About Blood Pressure?
Most elevated readings are not an emergency, but a few specific situations call for immediate action rather than waiting for your next appointment.
- Call 911 immediately if your reading is 180/120 mmHg or higher AND you have chest pain, shortness of breath, back pain, numbness or weakness, vision changes, or difficulty speaking — these are signs of a hypertensive emergency that can cause organ damage.
- Recheck, then call your doctor the same day if your reading is 180/120 mmHg or higher but you have no other symptoms. Sit quietly for five minutes and retest; if it is still that high, contact your doctor right away rather than waiting to see if it drops on its own.
- Schedule an appointment if your home readings are consistently above your personal target range across several checks, even without symptoms — this may mean your treatment plan needs to be reassessed.
- Seek same-day care if a high reading is accompanied by sudden dizziness, fainting, or a severe headache that feels different from your usual headaches.
How Can You Lower Blood Pressure Naturally?
Lifestyle modifications are highly effective for managing elevated blood pressure and serving as first-line therapy for early-stage hypertension. When implemented consistently, these evidence-based strategies can reduce systolic pressure by 5 to 20 mmHg, potentially reducing or eliminating the need for pharmacological treatment. Key lifestyle protocols include:
- Sodium Restriction and Potassium Optimization: Restrict daily sodium intake to less than 1,500 to 2,000 mg, while increasing potassium intake to 3,500 to 4,700 mg through a diet rich in leafy greens, avocados, and bananas. This dietary balance helps the kidneys excrete sodium, reduces blood volume, and promotes direct vascular relaxation.
- The DASH Eating Plan: Focus on the Dietary Approaches to Stop Hypertension (DASH) eating pattern, prioritizing whole grains, lean proteins, vegetables, and low-fat dairy. This diet is rich in calcium and magnesium, minerals that act as natural calcium channel blockers, relaxing vascular smooth muscle and lowering peripheral resistance.
- Cardiovascular Exercise: Engage in at least 150 minutes of moderate-intensity aerobic exercise, such as brisk walking, which offers the key health benefits of walking 30 minutes a day, cycling, or swimming, weekly. Physical activity stimulates nitric oxide production, improving vascular elasticity and lowering resting heart rate. You can determine your target aerobic zones using our free target heart rate calculator.
- Sleep Optimization: Maintain a consistent sleep schedule to ensure 7 to 9 hours of quality sleep nightly. Chronic sleep restriction disrupts the circadian rhythm, elevating nighttime cortisol and sympathetic activity, which contributes to arterial stiffening.
Daily Blood Pressure Tracking Routine
Integrating healthy habits into a structured daily routine supports natural circadian rhythms and helps manage blood pressure fluctuations. This chronological protocol is designed to promote cardiovascular health throughout the day:
- Morning (Waking): Wake up and sit quietly for a few minutes. Avoid immediate intense exertion or caffeine, as cortisol levels naturally spike upon waking, raising blood pressure. Measure your baseline blood pressure using a validated upper-arm cuff. Drink 16 ounces of water to reverse overnight dehydration and support blood volume dilation.
- Mid-Day (Lunch): Choose a low-sodium, nutrient-dense lunch matching the DASH diet profile, such as a large salad with grilled chicken and avocado. If your job is sedentary, stand up and walk for two to three minutes every hour to stimulate blood flow and endothelial nitric oxide release.
- Afternoon (Exercise): Complete 30 minutes of moderate aerobic exercise. If a snack is needed, choose potassium-rich foods like a banana or raw almonds to support vascular relaxation.
- Evening (Dinner & Wind Down): Prepare a light, low-sodium dinner at least three hours before bed. Measure your evening blood pressure. Turn off digital screens one hour before sleep to support natural melatonin release, helping lower nighttime heart rate and blood pressure. Aim for 7 to 9 hours of sleep.
Blood Pressure Self-Tracking Checklist
Use this weekly checklist to monitor your daily execution of blood-pressure-stabilizing habits:
- [ ] Home BP Logs: Did I measure and record my blood pressure in the morning and evening today?
- [ ] Proper Cuff Posture: Did I follow the correct posture guidelines (feet flat, back supported, arm at heart level, quiet) during measurements?
- [ ] DASH Nutrition: Did I limit my sodium intake to under 2,000 mg and consume at least 3 servings of potassium-rich foods today?
- [ ] Vascular Perfusion Walk: Did I complete at least 20 to 30 minutes of aerobic exercise or a brisk post-meal walk today?
- [ ] Circadian Sleep Hygiene: Did I sleep 7 to 9 hours last night and maintain a consistent waking time?
- [ ] Stress Calibration: Did I dedicate at least 10 minutes to deep breathing, meditation, or stress-reduction techniques today?
Expert Clinical Insights
Watch these educational videos from leading medical organizations to understand the clinical guidelines for home blood pressure measurement and cardiovascular health:
Frequently Asked Questions
What is the average blood pressure for a 25-year-old male?
A 25-year-old man falls in the 18-to-39 age band, where the average U.S. adult reading is about 119/70 mmHg, based on CDC NHANES data. That is a population average, not a personal target. The clinical goal for a healthy adult at any age is under 120/80 mmHg, so an average 25-year-old man is already close to that goal.
What is normal blood pressure for a 22-year-old male?
The same 18-to-39 average applies: about 119/70 mmHg. The clinical target stays under 120/80 mmHg regardless of the exact age within that range, since one year of age in your 20s does not meaningfully change vascular risk.
Does normal blood pressure change with age?
The population average rises gradually with age because arteries stiffen over time, but the clinical target for adults does not change. Under 120/80 mmHg is the goal at 25, 45, and 65. What changes by age is how clinicians weigh the risks of treatment, especially past 60 or 70.
What is considered a normal blood pressure range?
For adults, normal is under 120/80 mmHg, per the 2017 ACC/AHA guideline. Elevated is 120 to 129 systolic with diastolic under 80. Stage 1 hypertension starts at 130/80. Stage 2 starts at 140/90. These categories apply at every adult age.
Is blood pressure different for men and women at the same age?
Yes, before menopause. Estrogen has a protective, blood-vessel-relaxing effect, so women in their 20s and 30s average slightly lower readings than men the same age (about 110/68 versus 119/70). After menopause, that protection fades, and women's average readings often catch up to or pass men's.
What is normal blood pressure for a 70-year-old?
Adults 60 and older average about 133/69 mmHg (men) or 139/68 mmHg (women) in U.S. population data, though many clinicians still target under 130/80 when it is safe to do so. Diastolic pressure often drops slightly after 60 even as systolic keeps climbing, which is why older adults get individualized targets rather than one fixed number.
What is normal blood pressure for a child?
A child's normal blood pressure depends on age, sex, and height, not a single number. At the 50th percentile, systolic pressure runs roughly 86 to 94 mmHg for ages 1 to 5 and 94 to 105 mmHg for ages 6 to 12. A pediatrician plots your child's exact percentile using the full reference tables.
Why does blood pressure rise with age?
Mostly arterial stiffening. Decades of pulsing blood flow gradually break down elastin in artery walls and replace it with stiffer collagen, so the same heartbeat pushes pressure higher. This is also why systolic pressure rises more with age than diastolic pressure, which can even decline slightly after 60.
Related Reading by Life Stage
Want more detail for a specific age? These companion guides go deeper on the lifestyle factors, screening advice, and clinical nuance for each stage of life:
- Blood Pressure in Children and Teens: What's Normal by Age
- Blood Pressure in Your 20s and 30s: What's Normal and What to Watch
- Blood Pressure in Your 40s and 50s: Why It Creeps Up and What to Do
- Blood Pressure After 60: Targets, Risks, and When Lower Isn't Better
Scientific References
- Whelton PK, et al. 2017 ACC/AHA/AAPA/ABC/ACPM/AGS/APhA/ASH/ASPC/NMA/PCNA Guideline for the Prevention, Detection, Evaluation, and Management of High Blood Pressure in Adults. Journal of the American College of Cardiology.
- Mancia G, et al. 2023 ESH Guidelines for the management of arterial hypertension. Journal of Hypertension.
- Sacks FM, et al. Effects on blood pressure of systemic dietary patterns and sodium intake (DASH-Sodium Trial). New England Journal of Medicine.
- World Health Organization. Guideline for the pharmacological treatment of hypertension in adults. Geneva: WHO.
- Wright JD, et al. Mean Systolic and Diastolic Blood Pressure in Adults Aged 18 and Over in the United States, 2001-2008. National Health Statistics Reports, No. 35. CDC/NCHS.
- Flynn JT, et al. Clinical Practice Guideline for Screening and Management of High Blood Pressure in Children and Adolescents. Pediatrics 2017;140(3):e20171904. American Academy of Pediatrics.
Medical Disclaimer: This article is for general educational purposes only and does not constitute professional medical advice, diagnosis, or treatment. Always consult a qualified healthcare provider with questions about a medical condition. Do not stop or start medications without clinical supervision. See our full Medical Disclaimer and Editorial Policy.

Ganesh G Kamble
Ganesh G. Kamble is the founder and editor of Health is Heaven. He built this site after losing his father to a preventable condition, with the mission of providing clear, trackable health indicators so others can act early. His background is in the IT industry (16 years as an enterprise consultant) and he is not a medical professional; all medical content, formulas, and guides are reviewed by a credentialed medical reviewer/board before publication.