
Medically reviewed by: Health is Heaven Medical Review Board | Published by Ganesh G Kamble, Health is Heaven | Published: April 22, 2026 · Last updated: August 28, 2026
Calculate Your Pancreatic Workload
Before starting an insulin-lowering protocol, establish your baseline metrics. Visceral fat accumulation is the primary driver of peripheral insulin resistance, which can often be identified early by looking for skin signs of insulin resistance. Use our clinical calculators to map your body composition and assess your diabetes risk profiles:
What Is High Fasting Insulin?
To reduce fasting insulin levels naturally, we must understand the cellular biology of insulin signaling. Under normal metabolic conditions, the beta cells of the pancreatic islets of Langerhans synthesize and store insulin. When glucose enters the bloodstream, it enters beta cells via GLUT2 transporters, initiating a cascade: glucose metabolism increases the intracellular ATP-to-ADP ratio, closing ATP-sensitive potassium (K-ATP) channels. This depolarizes the cell membrane, opening voltage-gated calcium channels, which triggers calcium-mediated exocytosis of insulin granules into the bloodstream.
Once in Circulation, insulin binds to the extracellular alpha subunits of the insulin receptor, a transmembrane glycoprotein with intrinsic tyrosine kinase activity. Binding induces autophosphorylation of the beta subunits, which recruits and phosphorylates insulin receptor substrates, primarily IRS-1 and IRS-2. This activates the phosphatidylinositol 3-kinase (PI3K) pathway, initiating the translocation of glucose transporter type 4 (GLUT4) vesicles from intracellular pools to the cell membrane. This process allows glucose to enter skeletal muscle and adipose tissues, maintaining metabolic homeostasis.
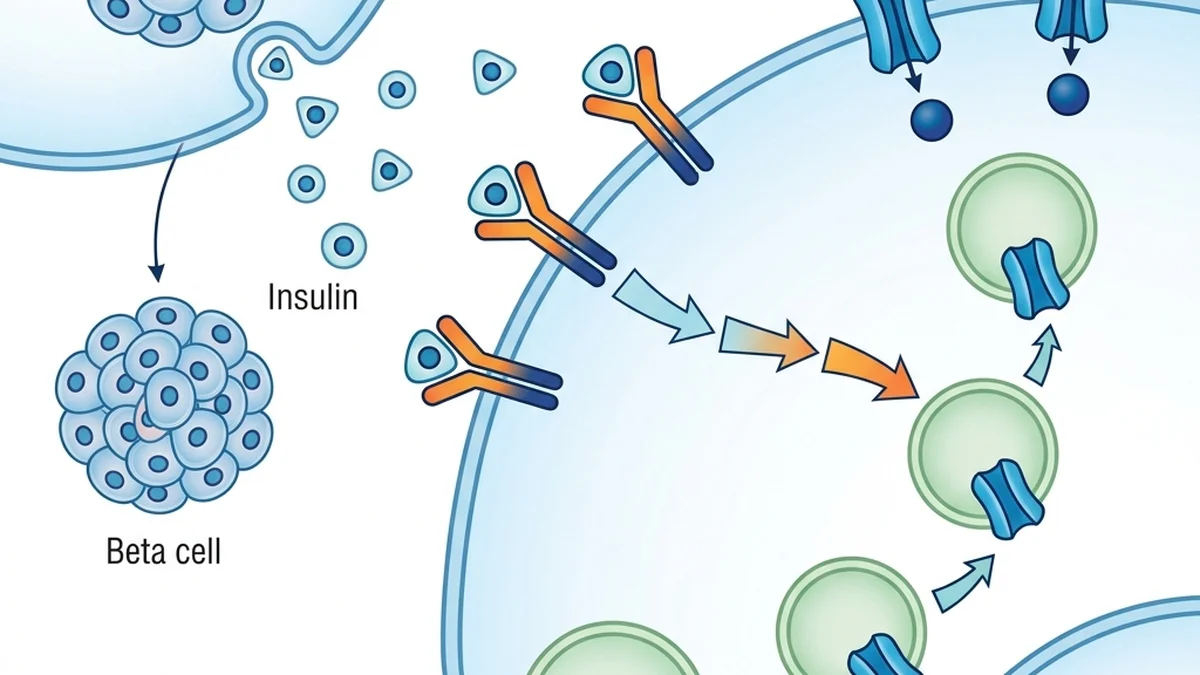
In hyperinsulinemia, this pathway degrades. Chronic overexposure to carbohydrates and elevated systemic fatty acids triggers sustained insulin elevation. In response, cells downregulate the number of active insulin receptors on their membranes. Recent research from 2026 demonstrates that to catch these metabolic shifts early, monitoring your baseline glycemic volatility and referencing a normal cgm range for non diabetics can reveal hidden post-meal glucose excursions even when standard fasting glucose appears normal. These continuous glucose monitoring insights provide unprecedented precision in identifying insulin resistance before it manifests as clinical hyperglycemia. Furthermore, inflammatory cytokines such as TNF-alpha and IL-6, along with elevated free fatty acids, stimulate serine kinases. These kinases phosphorylate serine residues on IRS-1 and IRS-2, preventing normal tyrosine phosphorylation and blocking the signal to translocate GLUT4 transporters to the membrane, which traps glucose in the bloodstream and forces the pancreas to produce more insulin to compensate. To interrupt this chronic pathway, implementing intermittent fasting for beginners or utilizing healthy recipes for diabetes management can facilitate metabolic switching and rest pancreatic beta-cells, restoring insulin receptor sensitivity over time. Over extended periods, the constant demand on the pancreatic islets can lead to beta-cell hypertrophy and eventual exhaustion, shifting the clinical presentation from hyperinsulinemia to absolute insulin deficiency.
Why High Fasting Insulin Is Dangerous
The term allostatic load refers to the cumulative wear and tear on body systems resulting from chronic overactivity of physiological stress responses. Sustained hyperinsulinemia is a significant driver of allostatic overload, causing damage across multiple organ systems:
- Vascular Endothelial Stiffening: Insulin stimulates endothelial nitric oxide synthase (eNOS) to produce nitric oxide, promoting vasodilation. However, in insulin-resistant states, the PI3K pathway is impaired, while the mitogen-activated protein kinase (MAPK) pathway remains active. The MAPK pathway stimulates endothelin-1, a potent vasoconstrictor, promoting vascular stiffening, arterial plaque stability issues, and hypertension. This explains the strong epidemiological correlation between elevated insulin and cardiovascular disease events.
- Hepatic Lipogenesis: Chronic insulin elevation keeps the sterol regulatory element-binding protein 1c (SREBP-1c) pathway active in the liver, driving de novo lipogenesis. This converts excess carbohydrates into saturated fatty acids, leading to non-alcoholic fatty liver disease (NAFLD, now clinically classified as MASLD) and worsening hepatic insulin resistance. As hepatic fat accumulation accelerates, the liver becomes resistant to insulin's signal to suppress gluconeogenesis, causing elevated glucose output even during overnight fasting states.
- Adipose Dysfunction and Visceral Accumulation: High insulin levels suppress hormone-sensitive lipase (HSL), blocking lipolysis and preventing the mobilization of fatty acids for fuel. Concurrently, insulin upregulates lipoprotein lipase (LPL) in visceral fat depots, routing lipids into omental fat stores, which release inflammatory cytokines. This creates a pathological feedback loop, as the inflamed visceral fat secretes higher levels of free fatty acids directly into the portal vein, further accelerating hepatic insulin resistance.
How to Lower Fasting Insulin Naturally: 5 Evidence-Based Protocols
Lowering fasting insulin levels requires structured metabolic interventions. Below are six endocrinology-backed protocols designed to restore receptor sensitivity and reduce pancreatic strain.
1. Walk After Meals
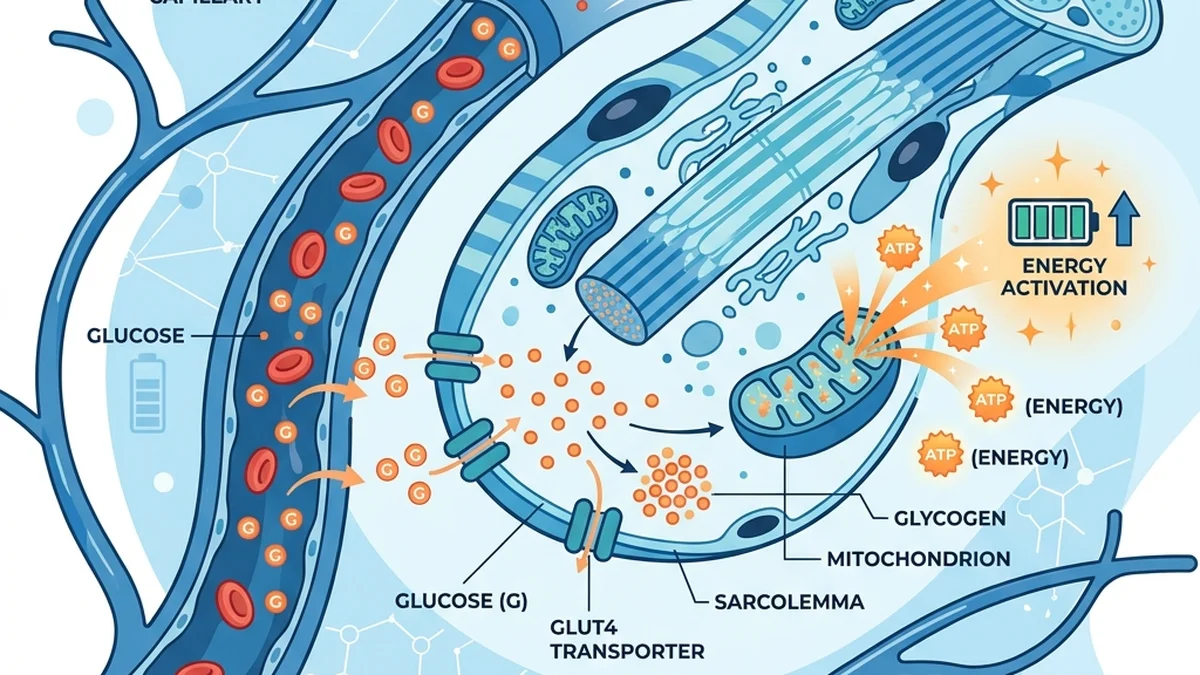
Skeletal muscle accounts for roughly 80% of insulin-stimulated glucose disposal. During physical inactivity, glucose entry into muscle depends on the insulin-signaling cascade. However, muscular contraction activates an independent pathway. When skeletal muscle contracts, the intracellular AMP-to-ATP ratio rises, activating AMP-activated protein kinase (AMPK). Activated AMPK stimulates the translocation of GLUT4 vesicles to the cell membrane, bypassing the insulin receptor entirely. This allows active muscles to clear glucose from Circulation without requiring insulin release. The rate of glucose clearance is dependent on the recruitment of different muscle fibers, with Type I (slow-twitch) fibers utilizing glucose primarily for oxidative metabolism, and Type II (fast-twitch) fibers storing it as glycogen after high-intensity glycolytic work.
2. Stop Snacking Between Meals
Popular nutrition advice from decades past encouraged frequent small meals and snacks to "keep metabolism stoked." Mechanistically, this advice is precisely backward for anyone managing elevated fasting insulin. Every time food (particularly carbohydrate or protein) is consumed, insulin is released, and it remains elevated for one to three hours afterward. Constant grazing throughout the day means insulin is rarely, if ever, allowed to fall to its baseline trough, keeping fat cells locked in storage mode around the clock and denying the pancreas any recovery window.
Consolidating intake into two to three defined meals, with true fasting gaps between them, allows insulin to fall to baseline for meaningful stretches of the day. This is the physiological rationale behind intermittent fasting for beginners as an insulin-management tool specifically, distinct from its use for weight loss. The length of the daily eating window matters less than the consistency of achieving a genuine insulin trough — even a 12-hour overnight fast, extended gradually toward 14-16 hours as tolerated, produces a measurable reduction in average daily insulin exposure.
3. Reduce Belly Fat
Excess fat does not only accumulate under the skin; it also accumulates ectopically inside and around the liver and pancreas. Fat infiltration of the liver drives continuous hepatic glucose output even when insulin is elevated (hepatic insulin resistance), forcing the pancreas to secrete still more insulin to compensate. Fat infiltration of the pancreas itself can directly impair beta-cell insulin secretion capacity. This self-reinforcing cycle — sometimes described in the research literature as the liver-pancreas "twin cycle" of hyperinsulinemia — means that reducing visceral and organ-level fat, not just body weight generally, is one of the most direct levers for lowering fasting insulin. Our hepatic function and fatty liver disease guide covers this mechanism, and its resolution, in more depth.
4. Do Resistance Training
Beyond the acute, insulin-independent GLUT4 translocation described above, resistance training has a second, slower-acting benefit: it increases total muscle mass, which directly increases the body's total glycogen storage capacity. A larger glycogen reservoir means a given carbohydrate load requires proportionally less insulin to be fully stored, lowering the average day-to-day insulin burden. This compounds with the postprandial-walking effect described earlier — walking clears glucose acutely after a specific meal, while resistance training raises the body's baseline glucose-handling capacity for every meal going forward.
Frequently Asked Questions About Fasting Insulin
5. Fix Your Sleep
Sleep restriction elevates evening cortisol and blunts the deep-sleep growth hormone pulse that normally supports insulin sensitivity overnight. Even a few consecutive nights of short sleep can measurably raise next-day fasting insulin in otherwise healthy adults. Tracking accumulated sleep debt with our sleep debt calculator can reveal whether poor sleep, rather than diet alone, is sustaining an elevated fasting insulin reading.
These protocols compound rather than compete: restoring genuine insulin troughs between meals, reducing visceral and organ-level fat, expanding glycogen storage capacity through resistance training, and protecting sleep all act on different points of the same feedback loop. None of them replace a fasting insulin or HOMA-IR test from your physician to establish where you are starting from and to track progress over months, not days.
What is a normal fasting insulin level?
There is no single universally-adopted cutoff, but many metabolic specialists consider fasting insulin under roughly 5-6 microIU/mL optimal, with levels above 10 microIU/mL suggesting meaningful insulin resistance even when fasting glucose is still normal. Always interpret your result with your physician, since reference ranges vary between labs.
Why does my doctor only test blood sugar and not fasting insulin?
Standard screening panels prioritize fasting glucose and HbA1c because they are cheaper, more standardized, and are the official diagnostic criteria for diabetes. Fasting insulin is a earlier, more sensitive marker of developing insulin resistance, but it is not yet a routine part of standard screening guidelines, so patients often need to specifically request it.
How is fasting insulin different from fasting blood sugar?
Fasting blood sugar measures the glucose actually circulating in blood, which the body works hard to keep in a narrow normal range for years by secreting more and more insulin. Fasting insulin measures how hard the pancreas is working to hold that glucose steady — it typically rises years before fasting glucose does, making it an earlier warning sign.
Is intermittent fasting the best way to lower fasting insulin?
It is one effective, well-supported tool because it restores genuine insulin troughs between meals, but it works best combined with reducing visceral/liver fat, resistance training, and adequate sleep rather than as a standalone fix. It is also not appropriate for everyone (including some people with diabetes on certain medications) without medical guidance.
Can you have high insulin with normal blood sugar?
Yes — this is called compensated insulin resistance or hyperinsulinemia, and it is very common. The pancreas is secreting extra insulin specifically to keep glucose in the normal range; blood sugar typically only rises once the pancreas can no longer keep up with that compensatory demand, often years later.
How long does it take to lower fasting insulin naturally?
Meaningful improvement typically takes weeks to a few months of sustained change, since it depends on measurable reductions in visceral/liver fat and improved muscle glucose disposal capacity, not just a single good day of eating. Retesting fasting insulin every 8-12 weeks is a reasonable way to track real progress.
Does stress raise fasting insulin?
Indirectly, yes. Chronic stress elevates cortisol, which raises blood glucose through hepatic glucose output, and the pancreas responds by secreting more insulin to compensate — so unmanaged stress can sustain elevated fasting insulin even with a good diet.
Sources
- Taylor R. Banting Memorial Lecture 2012: reversing the twin cycles of Type 2 diabetes. Diabetic Medicine, 2013.
- DeFronzo RA. Insulin resistance, hyperinsulinemia, and the road to type 2 diabetes. Kidney International, 2000.
- Richter EA, Hargreaves M. Exercise, GLUT4, and skeletal muscle glucose uptake. Physiological Reviews, 2013.
- Spiegel K, et al. Impact of sleep debt on metabolic and endocrine function. The Lancet, 1999.
Medical Disclaimer: This article is for general educational purposes only and does not constitute professional medical advice, diagnosis, or treatment. Always consult a qualified healthcare provider before changing your diet, exercise routine, or fasting practices, especially if you have diabetes or take glucose-lowering medication. See our full Medical Disclaimer and Editorial Policy.

Ganesh G Kamble
Ganesh G. Kamble is the founder and editor of Health is Heaven. He built this site after losing his father to a preventable condition, with the mission of providing clear, trackable health indicators so others can act early. His background is in the IT industry (16 years as an enterprise consultant) and he is not a medical professional; all medical content, formulas, and guides are reviewed by a credentialed medical reviewer/board before publication.